Helpline

0300 111 1234

ADPKD research priorities

ADPKD research priorities

ADPKD research priorities

The views of people affected by ADPKD are vital when deciding what to research. We asked the James Lind Alliance (who specialise in prioritising research) to help us prioritise the views of people affected by ADPKD (either directly or due to ADPKD in their family) and healthcare professionals.

To find the top 10 priorities, we funded a research Priority Setting Partnership (PSP), overseen by a steering group which included people living with and affected by ADPKD, healthcare professionals and the James Lind Alliance

We summarised 117 questions about ADPKD care and management that hadn't been answered by research into a shortlist of 35. We asked patients, family members, carers and healthcare professionals to rank which of the 35 questions were the most important to them. Over 700 people replied to our survey. The Top 10 research questions below are the result.

Read the ADPKD research priorities report (PDF, 737 KB) for more detail on each of these priorities and how we arrived at the Top 10.

Read the BMJ Open Paper.

Our next step is to encourage researchers to use the Top 10 list (and the other questions that didn’t make the top 10) to inform their research plans. 

The Top 10

  • 1. What treatments can be developed that slow or prevent progression of ADPKD and improve patients’ quality of life?

    ADPKD gets worse over time, causing damage to the kidneys. This is called progression.

    Most treatments that people with ADPKD receive can reduce symptoms but don’t prevent the disease progressing.

    For many people, damage to the kidneys eventually means they will need dialysis or a kidney transplant.

    ADPKD can also cause other health problems as it progresses. Tolvaptan (Jinarc®) is the only treatment available that can help to slow ADPKD progression in some patients.

    This research question aims to find new treatments that can slow or prevent ADPKD progression and so improve patients’ lives.

  • 2. Which people with ADPKD would benefit from early treatment and how can doctors identify them?

    For some people, early treatment may slow the progression of ADPKD and reduce the problems it causes.

    For other people, some treatments may not work as well or might cause too many side effects.

    This research will help doctors identify the people who will benefit from each treatment.

    This means patients can start to benefit from the right treatment sooner.

  • 3. What are the best ways to organise the care of people with ADPKD to improve their outcomes?

    ADPKD doesn’t only affect the kidneys — it can affect other parts of the body too, such as the liver.

    This means people with the disease usually need to see a range of doctors specialising in different parts of the body during their lives.

    Some people with ADPKD tell us that they experience inconsistencies or gaps in their care.

    This can leave people frustrated and unsure whether they are getting the best care.

    This research question aims to work out the best ways that different specialists providing care to people with ADPKD can work together consistently to support their patients’ health.

  • 4. What effect does pregnancy have on women with ADPKD including their pregnancy health, kidney function, and liver cysts?

    We do not know much about how pregnancy affects the bodies of women with ADPKD.

    For example, does carrying a baby cause extra damage to the kidneys of women with ADPKD?

    Can it make their liver cysts grow faster?

    Based on this research, doctors will be able to give women with ADPKD a clearer picture of any risks of pregnancy to them and their babies.

    This research may also help to work out which treatments could reduce the chance of these problems occurring.

  • 5. What are the benefits and harms of drugs that can be used for the management of ADPKD including polycystic liver disease (PLD)?

    There are a number of treatments to help manage ADPKD. For patients to be able to choose between the different treatments they are offered, they need to know the possible benefits and side
    effects of each.

    Yet there is not much research on risks and benefits, making it hard for healthcare professionals to give detailed advice on this.

    This research will give patients and healthcare professionals a clearer picture of the benefits and risks of each treatment so they can be confident in selecting the right one together.

  • 6. For people with ADPKD experiencing pain, what treatments work best to reduce this pain?

    Kidney pain caused by ADPKD can be disabling and have a big impact on people’s lives. ADPKD pain can be hard to treat.

    Sometimes the source of the pain (such as a cyst infection) is difficult to find or treat.

    If researchers can discover which treatments are most effective for ADPKD pain, they can make a massive difference to some people’s lives.

  • 7. What changes to lifestyle, exercise and/or diet (including amount of water drunk) benefit people with ADPKD and polycystic liver disease (PLD)?

    Many people with ADPKD want to know what steps they can take to stop their disease worsening. We know that a healthy lifestyle and certain changes to diet (for example, not eating too much salt) can help.

    We don’t have all the answers yet though, such as whether drinking a lot of water helps to keep the kidneys healthy.

    This research can provide those answers, and so help people with PKD to take more active steps to protect their health and be in control of their disease.

  • 8. When people are newly diagnosed with ADPKD, how does this affect them psychologically and what impact does it have on their life? What information and support would help people at this time?

    A diagnosis of ADPKD can turn your life upside down and trigger a wide range of emotions.

    Getting the right information and support can make an enormous difference. It can help you to cope, feel in control, and plan positively for the future.

    People with ADPKD tell us that we still have more to do in this area.

    This research will give people with ADPKD the chance to be heard. The results will mean better information and support for all patients, whether newly diagnosed or living with ADPKD for some time.

  • 9. What are the benefits and harms of screening for and diagnosing ADPKD in children and young people (up to 18 years) at risk of having inherited this condition?

    Tests are available to check for ADPKD in people who might have inherited the condition. This is called screening.

    Screening for ADPKD in children who might have inherited the condition has some clear benefits. For example, children found to have ADPKD can begin to receive any treatments that might help. However, screening can also cause harm, such as making children and their parents anxious about their health and future.

    This research will explore the benefits and harms of screening children. It will help us to understand which benefits and harms are most important to children, young people, and their families. The results will help similar people in the future choose whether or not they want to have screening tests.

  • 10. What causes enlarged blood vessels (aneurysms) in some people with ADPKD and what is the most effective way to screen for and treat aneurysms?

    ADPKD can increase the risk of getting a swollen blood vessel (an aneurysm), particularly in the brain.

    Brain aneurysms often don’t cause a problem, but in some people they burst and bleed, which can cause a stroke or death. This makes aneurysms a source of great fear for some people with ADPKD, especially if other family members have had one. Some procedures can treat aneurysms before they burst.

    This research will help us to understand more about aneurysms: why they occur in people with ADPKD, how they can be spotted early (through screening), and how they can be treated.

    This research could save lives, reduce disability and reduce the anxiety that aneurysms cause.

You can see the shortlist of 35 questions, with the underlying list of 117 research uncertainties, on the website of the James Lind Alliance.

Read the ADPKD PSP scope here.

Thank you!

We would like to thank everyone with ADPKD, family member, carer, and healthcare professional who took part in this PSP and the James Lind Alliance facilitators. Without their time and opinions, this PSP would not have been possible. To get involved or for more information about our research priorities, do get in touch here [email protected]

Current partners

Read more …ADPKD research priorities

  • Hits: 15392

Apply for a research grant

Apply for a research grant

Apply for a research grant

PKD Charity Grant Programme

In 2025 after years of conversations and planning, we established the PKD Partnership — a bold collaboration between PKD Charity and Kidney Research UK. It’s built on our shared determination to accelerate progress in PKD research and improve outcomes for patients and families.

By working with researchers, clinicians, patients and industry, the PKD Partnership is creating a UK-wide programme that unites scientific expertise and lived experience to develop better treatments and brighter futures.

As we move forward our grant funding activity will be delivered through grant calls made by the PKD Partnership.

We’re calling on researchers, clinicians, and early-career scientists — from both PKD and other disease areas — to join us in transforming care for people with PKD.

This first round of funding from the PKD Partnership is now open, designed to support high-quality, collaborative science that accelerates discoveries, unlocks new treatments, and offers real hope to families. Researchers whose work aligns with the biological pathways involved in PKD — such as inflammation, healing, fibrosis, or imaging technologies — are encouraged to apply. Applications from early-career researchers and allied health professionals are also welcome.

  • Open for applications: 11 August 2025
  • Deadline: 22 October 2025

Applications are open for a range of research funding opportunities — from pilot grants and PhD studentships to clinical and non-clinical fellowships — supporting both early-stage ideas and larger, ambitious projects aligned with our strategic priorities.

Grants range from £10,000 for early pilot studies to up to £250,000 for major research projects. Additional funding is available for fellowships and studentships.

Proposals should address one or more of the PKD Partnership’s strategic priorities:

  1. Biomarker and molecular insights
    Identify and validate biomarkers to predict disease progression and treatment response.
  2. Preclinical innovation
    Advance reliable experimental platforms to accelerate therapeutic discovery.
  3. Integrated data and translational tools
    Leverage large-scale data and computational methods to improve outcomes.
  4. Personalised and preventive care strategies
    Develop tailored treatments and early interventions.

Collaboration between research centres is strongly encouraged.

Read about grants we have awarded

Read more …Apply for a research grant

  • Hits: 16325

Take part in a study

Take Part in a PKD Study

Take Part in a PKD Study

Advancing PKD Research: Be Part of the Breakthrough

PKD research advances better treatments, earlier diagnosis, and the hope of prevention. Studies have improved blood pressure management and led to therapies that can slow disease progression. Ongoing research helps scientists better understand how cysts grow and develop new medications to protect kidney function.

Taking part in a PKD study is a meaningful way to support this progress. Clinical trials and observational studies provide vital information about how the disease develops and how treatments work in real life. Participants may also benefit from access to new therapies and closer medical monitoring.

Each person who joins a study helps move the field closer to better outcomes and greater hope for future generations.

HIYA-PKD Study

High blood pressure (hypertension) can be an early sign of PKD, even in children.

The HIYA-PKD study is exploring how common high blood pressure is in children and young people at risk of Autosomal Dominant Polycystic Kidney Disease (ADPKD).

Researchers are looking for untested 12–17-year-olds who have a parent or sibling with PKD to take part. 

Find out more

IMPEDE-PKD

The IMPEDE-PKD trial is recruiting in the UK to explore whether metformin, a medication commonly used to treat diabetes, can help slow disease progression in people with Autosomal Dominant Polycystic Kidney Disease (ADPKD).

The trial is currently open at 34 UK centres. 

Find out more

Thank you for supporting our work

Your donation means we can fund vital PKD research.

Please Donate

Read more …Take part in a study

  • Hits: 18562

The ADPKD and ARPKD Registries

The ADPKD and ARPKD registries

Join the ADPKD
and ARPKD registries

Join the RaDaR registry

The RaDaR National Registry of Rare Kidney Diseases is a UK-wide database that collects medical information on people with rare kidney conditions, including autosomal dominant (ADPKD) and autosomal recessive polycystic kidney disease (ARPKD).

By bringing this information together, RaDaR helps researchers better understand how PKD develops and progresses in children and adults. It also supports faster, more effective research and clinical trials into new treatments.

Both ADPKD and ARPKD are supported by RaDaR Rare Disease Groups – teams of clinicians, researchers, and patient representatives working to improve care and quality of life for those affected.

Not every NHS hospital recruits to RaDaR—but your interest can help change that. Joining RaDaR benefits you today by connecting you to the latest developments, and it benefits the entire PKD community for years to come by shaping research, care, and treatment.

  • ADPKD Patient Registry

    If you receive ADPKD care at a UK hospital—or your child attends a specialist paediatric kidney centre—you may already have been invited to join RaDaR. If not, please enquire about joining.

    How to Join

    • Speak to your kidney doctor or nurse to check if your hospital has an active RaDaR programme.
    • If you’re unsure, email [email protected]
      with your hospital’s name to explore your options.
    • Learn more about RaDaR.

    Your Information
    All data in the RaDar Registry is stored securely and only shared with your consent. You can view your records at any time, and both you and your GP will receive occasional updates.

  • ARPKD Patient Registry

    If your child is treated at one of the UK paediatric kidney centres, you may already have been asked to register them on RaDaR. If not, please enquire about registering.

    Adults with ARPKD can also join RaDaR. 

    How to Join

    • Speak to your consultant or nurse to check if your hospital has an active RaDaR programme.
    • If you’re unsure, email [email protected]
      with your hospital’s name to explore your options.
    • Learn more about RaDaR.

    Your Information
    All data in the Registry is stored securely and only shared with your consent. You can view your records at any time, and both you and your GP will receive occasional updates.

Read more …The ADPKD and ARPKD Registries

  • Hits: 20205

PKD Charity & Kidney Research UK research partnership

PKD Charity & Kidney Research UK research partnership

PKD Charity & Kidney Research UK research partnership

PKD Charity (PKDC) and Kidney Research UK have launched a joint partnership to progress research in polycystic kidney disease (PKD).

PKD is a genetic condition where several cysts form and grow on various organs in the body, but mainly the kidneys. Affecting over 12 million people around the world and up to 70,000 adults and children in the UK, PKD is the most common genetic kidney disease and the fourth leading cause of kidney failure. There is currently no cure.

Our vision is to improve the health and quality of life of people affected by PKD. Together, we want to significantly improve PKD patient outcomes over the next ten years, through a joint research programme.

New PKD treatments are needed now, for people like Mae

Maegan Smith (Mae) knows only too well the impact PKD can have. Mae, her dad Wayne and sister Stephanie have autosomal dominant PKD. Wayne lost his own father to kidney disease when he was nine years old. When Wayne’s own kidneys failed, he received gruelling dialysis three times a week for two years – until he recently received a kidney transplant from an anonymous living donor. Mae and Stephanie, both in their twenties, go to hospital regularly to have their kidney function checked. 

Mae explains: “Most days I don’t think about my kidney disease because I have virtually no symptoms. But some days my mind wanders to my future and the reality hits me smack in the face like a truck. I’m hopeful that before our kidneys fail, new treatments will be available to control our condition. My biggest hope is that if we have our own children one day, they won’t have to live with the same fear of kidney disease that my family has for generations.”

Research is vital to give the family hope

Kidney research is critically underfunded - in the UK, less than 1% of all health research funding goes to kidney research, and a fraction of that amount goes towards PKD research specifically.

Kidney Research UK and PKD Charity want to address this and are working together to raise awareness and funds for their new joint research programme.

The two charities are perfectly placed for this work. Kidney Research UK is the largest charity dedicated to research into kidney disease in the UK – it funds work across the whole research pipeline, from better understanding the disease, through to new ways to prevent it. PKD Charity, as the voice of people with PKD, will help to design research into PKD, help to identify research priorities, provide stewardship, evaluate research progress and help disseminate information to patients.

By working together, we plan to build capacity and capability in PKD research by awarding grants to researchers for projects, studentships, or fellowships. We will bring together our research networks and share governance and programme management. We will make PKD research a priority that benefit patients with the condition. We aim to:

  • Increase our understanding of current and new biological pathways, develop new models and biomarkers to study the disease, and identify new ways to treat it
  • Explore the potential around genetics and cell therapies, genomics and use of data resources including the UK Rare Renal Registry RaDaR 
  • Move the evidence we gather through to the clinic, as it develops over the coming years 
  • Understand complications better, including pain, and develop new approaches towards treatments

Tess Harris, CEO of the PKD Charity, said:  "I am very excited by this collaboration, which is the result of discussions over several years between our two charities. I inherited ADPKD, along with my three siblings, from my father. I have witnessed the premature death of my father and a sister and have recently had a kidney transplant following a period on dialysis. I have an affected niece and nephew.
Over my 15 years with the PKDC, as a trustee and now CEO, I have had daily contact with PKD patients and family members. I have heard their often tragic and painful stories, their battles with the stress of diagnosis and the prospect of an inevitable future blighted by kidney failure or massive cystic livers."

She continues: “Research is critical to improving their lives. As a small charity, we've been able to fund a few important projects at early research stages, including a biobank of kidney tissue donated by PKD patients and families. Kidney Research UK has been a significant funder of PKD research over 30 years. Yet, the amount spent on PKD research is miniscule compared with amounts spent on cancer, whilst the burden and cost of healthcare for PKD patients and the social burden and costs on their families is disproportionately high. Coming together with Kidney Research UK means we can make research happen much faster.”

Sandra Currie, CEO of Kidney Research UK, said: “We are delighted to be launching our partnership with PKD Charity. The coronavirus pandemic has delayed our launch plans by around six months, and it has certainly challenged our plans to combine forces to raise the money we need. But the pandemic has highlighted the need and urgency for this research, because people living with PKD are more at risk of COVID-19. Now, we are even more determined to invest in more research into this significant area of kidney disease.”

Mae comments: “This joint research programme is a huge step forward for people like me living with PKD – it will hopefully drive some incredible research into this condition forward and give hope to so many. Living with this genetic condition is a huge burden with a turbulent future ahead. Having been part of the discussions from the beginning, I can see passion and excitement from both Kidney Research UK and PKD Charity, and I really hope the research will find a breakthrough that changes the future for people living with PKD and our children.”

  • About Kidney Research UK

    As the largest kidney research charity in the UK, nothing is going to stop us in our urgent mission to end kidney disease. We’re here to be heard, to make a difference, to change the future. This is a disease that ruins and destroys lives. It must be stopped. 

    Over the past 60 years, our research has made an impact. But kidney failure is rising, as are the factors contributing to it, such as diabetes and obesity. Today, we are more essential than ever. 

    Kidney disease affects three million people in the UK, treatments can be gruelling and currently there is no cure. Only research will end this and nobody can do it but us.

  • About the PKD Charity

    Formed in 2000 by a PKD patient and a kidney doctor, the PKD Charity supports those affected by PKD, their families and carers. We raise awareness and fund research. Our support services blend educational events held around the UK or on web platforms with personalised and peer support – online, face-to-face and by phone.

    We fund the PKD Biobank of donated tissue at the UCL Centre for Nephrology Royal Free – which has provided over 2,500 samples and methods to over 90 projects in the UK – and have supported the development of the UK Rare Renal Registry RaDaR.

    Our patient advocacy efforts have contributed to global guidelines and consensus publications which have helped improved the care of PKD children and adults worldwide.

About PKD

There are two major forms of PKD: 

  • ADPKD - autosomal dominant polycystic kidney disease 
  • ARPKD - autosomal recessive polycystic kidney disease 

ADPKD is the most common form of PKD; if someone has ADPKD, there is a 1 in 2 risk of passing it on to any children, meaning that many families have multiple generations of affected members. People with ADPKD can suffer throughout their lives from childhood. Two in three will experience hard-to-treat, disabling chronic pain and periodic acute pain. Nearly half of those with ADPKD will have kidney failure caused by massive cystic growth before they are 60 - requiring life-saving dialysis or a transplant. In the UK, around 1 in 10 people with a kidney transplant or on dialysis has ADPKD. Some adults will require a liver transplant and others will be at risk of devastating, life-threatening brain aneurysms. High blood pressure (hypertension) affects nearly everyone with ADPKD from an early age, with an associated increased risk of cardiovascular disease. There is only one licensed disease-modifying drug for ADPKD, which is not suitable for everyone. 

ARPKD is a rare and severe form of PKD, affecting one in every 20,000 children born in the UK. Sadly, about one baby in three with ARPKD dies from underdeveloped lungs, either during pregnancy or in the first four weeks after birth. Some children will have kidney failure in the first year of life and will need life-saving dialysis until they are able to receive a kidney transplant. A few children will also need a liver transplant owing to a complication called congenital hepatic fibrosis (CHF). Children with ARPKD commonly have very high blood pressure and impaired growth. ARPKD is usually considered a childhood disease; however, improved care means that many now live to adulthood, when they typically experience complications of CHF as well as kidney impairment. ARPKD currently has no licensed therapies.

Donate today to support our ambitious research partnership.

Please Donate

Read more …PKD Charity & Kidney Research UK research partnership

  • Hits: 19530

PKD bioresource bank

PKD bioresource bank

PKD bioresource bank

The PKD Charity Bioresource Bank was established at UCL Centre for Nephrology, Royal Free London NHS Foundation Trust in 2011 and is supported by an annual grant from the PKD Charity.

We want this unique bioresource to become crucial to laboratory research in the UK. The acceleration of PKD research depends on well-characterized human PKD and age-matched normal control tissues, cell lines and animal models that faithfully recapitulate the genotypic and phenotypic characteristics of PKD.

Figure 1: Haematoxylin and esosin stained section of human ADPKD kidney, P. Wilson

The PKD Bioresource Bank contains more than 8,000 cell, tissue, and fluid samples of autosomal dominant polycystic kidney disease (ADPKD), autosomal recessive polycystic kidney disease (ARPKD), plus age-matched control samples suitable for research purposes. To date, researchers from University and Kings’ Colleges London, the Institute of Child Health/Great Ormond Street Hospital, the Royal Free London, and Addenbrooke's Cambridge, have submitted successful applications for Bioresource Bank materials in frozen, live cell and/or fixed sectioned states to use for PKD research projects.

If you are a researcher in the UK and want more details of samples available, please contact us. Please note that, owing to Human Tissue Act regulations, we cannot send samples outside the UK.

How to donate a kidney or liver to the Bioresource Bank

Kidneys and livers from ADPKD and ARPKD patients can be donated to the Bioresource Bank. If you or a child is about to have a kidney or liver removed, please contact us immediately with the name of your surgeon and hospital. Professor Pat Wilson, the chair of our Research Advisory Board, will then contact the surgeon to make the arrangements.

Read more …PKD bioresource bank

  • Hits: 19133

Research

Research

We fund research that will increase understanding of polycystic kidney disease (PKD) and help improve the management and treatment of everyone affected by PKD.

Thank you for supporting PKD research

Please Donate

Read more …Research

  • Hits: 19499

Genetic counselling and testing for ARPKD

Genetic counselling and testing

This information is for people who have been offered a test for autosomal recessive polycystic kidney disease (ARPKD) for themselves or their child. It’s also for their families and friends.  

We explain the gene changes that cause ARPKD and how they’re inherited. We also explain how genetic testing is done and what genetic counselling is.  

Getting new information on ARPKD can cause worry, especially if you’ve just been told your child might have ARPKD. Please call our helpline on 0300 111 1234 if you’d like to talk to someone about ARPKD.

Contents

Key facts

  • ARPKD is a rare disease that’s inherited. This means that the genes causing it can be passed to a child from their parents. 
  • It’s usually caused by a change in a gene called PKHD1. 
  • A person needs to have a change causing ARPKD in both of their PKHD1 genes to have ARPKD. 
  • If a person only has 1 changed PKHD1 gene, this makes them a carrier. They don’t have ARPKD themselves. However, they could pass the changed gene on to their children.  
  • If 2 people who are both ARPKD carriers have a baby, there’s a 1 in 4 chance (25% chance) their baby will have ARPKD. 
  • Very rarely, a new gene change causing ARPKD can happen in a baby who doesn’t have 2 carrier parents. 
  • A genetic test can look for the gene changes that cause ARPKD.  
  • These tests are only available on the NHS to people at risk of having, or carrying, ARPKD. 
  • Before having genetic testing for yourself or your child, you can have genetic counselling. 
  • At genetic counselling, you’ll get information to help you decide whether to go ahead with the test. 
  • Genetic testing can usually confirm whether a person has ARPKD. Sometimes the results don’t give a clear answer. 
  • A genetic test can even be done during pregnancy if a baby might have ARPKD. 

What is a gene?

Genes are the instructions the cells in our bodies need to grow, divide and do their jobs. Genes are made of DNA — a long chain of molecules linked together to form a code. These codes act like recipes, telling our cells how to make different proteins. Proteins do most the work in our bodies.  

You have thousands of genes. You have 2 copies of each gene, 1 from each parent. 

A picture of DNA strands, which make up genes. By Geralt, CC0, via Wikimedia Commons.

Which gene changes cause ARPKD?

ARPKD is a rare disease that’s inherited. This means that the genes causing it can be passed to a child from their parents. You can’t catch ARPKD, and it’s not cancer.

ARPKD is usually caused by a change in a gene called PKHD1. Much less often, people with ARPKD have a change in the DZIP1L or CYS1 gene. To keep things simple, we’ll focus on the PKHD1 gene on this web page. Doctors sometimes call these gene changes ‘mutations’ or ‘variants’.

Remember that we all have 2 copies of each gene. A person needs to have a change causing ARPKD in both of their PKHD1 genes to have ARPKD.

If a person only has one changed PKHD1 gene, this makes them a carrier. They don’t have ARPKD themselves. However, they could pass the changed gene on to their children.

About one in every 70 people in the UK is an ARPKD carrier.

What’s the chance of 2 ARPKD carriers having a child with ARPKD?

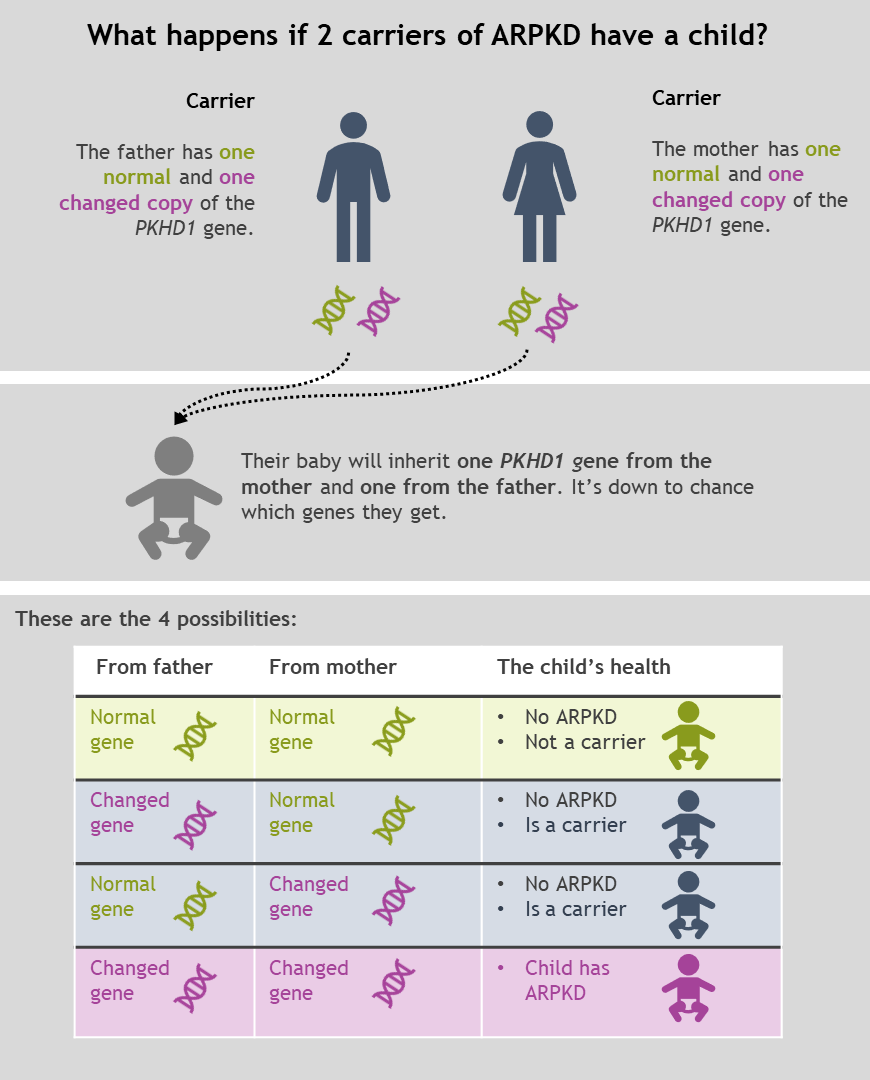
If 2 people who are both ARPKD carriers have a baby, there’s a 1 in 4 chance (25% chance) their baby will have ARPKD. The risk is the same each time they have a child together. 

There’s a 2 in 4 (50%) chance that their child will be a carrier.

There’s a 1 in 4 (25%) chance that their child won’t inherit any gene changes that cause ARPKD. This child can’t pass ARPKD on to their own children.

We show this in the diagram below.

Diagram showing the 4 possible outcomes if 2 carriers of ARPKD have a child, as explained in the text above

The 4 possible outcomes when 2 carriers of ARPKD have a child.

Can a child have ARPKD if only one of their parents is a carrier?

Yes, but the chance is very low.

Most people with ARPKD inherited changed PKHD1 genes from each parent.2 Much less often, a person inherited a changed PKHD1 gene from one parent and a change in their other PKHD1 gene happened by chance.

These new changes can happen in a father’s sperm or mother’s egg. They can also happen after conception (when a sperm fertilizes an egg). These new changes are sometimes called ‘spontaneous mutations’ or ‘de novo mutations’.

Out of 100 people with ARPKD, about 95 to 98 inherited a changed gene from each parent. About 2 to 5 in 100 have a new gene change that happened by chance.

What is genetic testing?

A genetic test can look for gene changes that cause health conditions.

A lab can do the test on any source of DNA. Usually, you give a blood sample. Doctors take other samples for genetic testing before birth — we explain this later.

In a genetics lab, a technician will use a machine called a sequencer to read the person’s DNA code. They’ll check the code for changes linked to ARPKD.

The technician might check the codes of specific genes linked to ARPKD and other kidney conditions. Or they might read a person’s entire DNA code. This is called ‘genomic testing’ (because a whole DNA code is called a genome). The genetics service should explain this to you beforehand.

Before having genetic testing for yourself or your child, you can have genetic counselling. Your GP or kidney doctor can refer you for this.

What is genetic counselling?

Genetic counselling is not the same as counselling for mental health issues. You could see a genetic counsellor, a clinical geneticist or a specialist genetic nurse. Some kidney doctors also provide genetic counselling.

They’ll give you information to help you decide whether to have a genetic test.

A seated man and woman in deep conversation in a contemporary office

You’ll talk through:

  • what ARPKD is
  • the pros and cons of genetic testing
  • the possible results
  • how the results could affect you and your family
  • how the gene could be inherited by future generations

People who are ARPKD carriers can also get advice on ways to have a child without ARPKD, if they choose.

After genetic counselling, you’ll choose whether you want to go ahead with the test. You don’t have to decide right away.

Expert Christine Patch tells us that having genetic counselling is very individual. People can react differently and make different choices. Your choices might be affected by:

  • your views on risk
  • your relationships with family members
  • how others in your family react and their views
  • the results of genetic tests

Families often find it hard to talk about genetic conditions and genetic testing. A specialist can give you and your family support on this.

Where will I have genetic counselling?

People usually go to their nearest NHS regional genetic centre for genetic counselling. Some centres organize clinics at local hospitals or health centres. This means you won’t need to travel as far.

When is genetic testing useful?

The signs and symptoms of ARPKD can be similar to some other kidney conditions that cause cysts. Experts say it’s best to do a genetic test if a developing baby (fetus), newborn baby or child has multiple kidney cysts.

You can learn more about signs and symptoms of ARPKD on our pages ARPKD in babies and ARPKD in children and adolescents.

Genetic testing, can be useful in these situations:

  • Your developing baby (fetus), newborn baby or child has signs of ARPKD. The test can usually confirm whether they have ARPKD or a different kidney condition.
  • You and your partner have a child with ARPKD and are planning to have another child. Genetic testing can confirm whether you’re both carriers and the risk of having another child with ARPKD.
  • If you and your partner are both carriers and you’re pregnant, you can have your developing baby (fetus) tested for ARPKD. You can decide whether to keep the pregnancy. If you go ahead, you and your pregnancy team can plan the right care for the birth.
  • If you and your partner are both carriers and want a child without ARPKD, you might be able to have a special type of fertility treatment called preimplantation genetic testing (PGT). Your embryos will be tested and one without ARPKD will be put in the mother’s womb.

A family of people of different generations.

Who can have genetic testing?

Genetic tests for ARPKD are only available on the NHS to people at risk of having (or carrying) ARPKD. These people include:

  • children and adolescents with signs of ARPKD
  • babies with signs of ARPKD before or after birth
  • parents and siblings of children with ARPKD
  • developing babies (fetuses) of parents who are both carriers of ARPKD

ARPKD is very rare. Genetic testing is not available to people who aren’t at risk.

If you have a child with ARPKD and want to check whether their brothers or sisters have the disease, they may be able to have genetic testing.

Alternatively, doctors can check for ARPKD using ultrasound scans and a blood pressure check.

If you have a relative with ARPKD but they aren’t your sibling or child, you can’t usually have genetic testing on the NHS. This is because being a carrier rarely matters. The chance of your partner also being a carrier is 1 in 70.

Taking samples for genetic testing during pregnancy

If doctors think your developing baby (fetus) might have ARPKD, you might be able to have them tested for ARPKD during pregnancy. This is usually done between weeks 11 and 20 of pregnancy.

Your pregnancy doctor (obstetrician) will collect a sample of your fetus’s DNA. The two main ways to do this are:

  • amniocentesis to take a sample of amniotic fluid
  • chorionic villus sampling (CVS) to take a sample of cells from the placenta

We explain these procedures below. With either procedure, there’s a small risk of losing the pregnancy.

A specialist might also be able to say whether your baby is likely to have ARPKD using an ultrasound scan.

If tests show that your developing baby has ARPKD, you can choose whether to keep or end the pregnancy. This can be an extremely hard decision for parents and support is available. We talk about this on our web page on ARPKD in babies.

Call our helpline on 0300 111 1234 for support and advice. You can also contact us by email at [email protected] or on Facebook messenger.

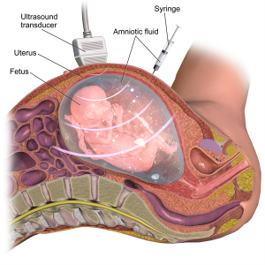
Amniocentesis

For amniocentesis, a doctor uses a needle to take a sample of fluid from your womb (the amniotic fluid). They’ll use an ultrasound scan to see where they’re putting the needle. We show this in the picture below.

The test is usually uncomfortable but not painful.

You can usually have this test at weeks 15 to 20 of pregnancy.

The NHS has more information on amniocentesis.

A drawing showing the process of amniocentesis, as described in the text above

Drawing of amniocentesis. Picture from Creative Commons (Attribution-Share Alike 4.0 International license).

Chorionic villus sampling (CVS)

CVS is similar to amniocentesis, but the sample of cells is taken from the placenta [NHS CVS]. Your pregnancy doctor might put the needle through the opening to your womb (cervix) rather than through your abdomen.

The test is usually uncomfortable but not painful.

You can usually have this test at weeks 11 to 14 of pregnancy.

The NHS has more information on CVS.

How long does it take to get genetic test results?

If you or your child are the first people in your family to have genetic testing for ARPKD, the results could take a couple of months or more. If the gene change running in your family is already known, for example when undergoing genetic testing in pregnancy, your test result might come in 2 weeks. This is because the lab technicians will know which gene change they’re looking for.

What could the results of the test be?

If a person has ARPKD, genetic testing can usually find the cause.

For every 100 people with ARPKD who have testing, gene changes causing ARPKD are found in about 70 to 85 people (70–85%).

Here are the possible outcomes in more detail:

  • The lab finds changes known to cause ARPKD in both PKHD1
  • The lab finds a change in one PKHD1 They can’t find a change in the second PKHD1 gene.
  • The lab can’t find any gene changes known to cause ARPKD.
  • The lab finds an unusual code in the PKHD1 This code hasn’t been seen in other people and doctors aren’t sure whether it can cause ARPKD.

There’s also a small chance the lab will find a change in a different gene linked to ARPKD (DZIP1L or CYS1).

If you have a child with ARPKD but genetic testing doesn’t find any gene changes, you might still be able to have testing in future pregnancies. The lab will compare your DNA sample with those taken from your embryos or fetus.

Can genetic tests help doctors predict how severe a person’s ARPKD will be?

It’s hard for doctors to predict how severe a person’s ARPKD will be based on their genetic test results. This is because people with the same gene change sometimes have different ARPKD symptoms at different ages.

If both PKHD1 genes have changes called ‘truncating mutations’, ARPKD is usually severe. For other PKHD1 changes, doctors can’t always predict how severe ARPKD will be.

In one study, people with changes in the DZIP1L gene had milder ARPKD. They had kidney cysts but no liver cysts.

Your kidney specialist might be able to estimate how severe your baby’s or child’s ARPKD will be based on:

  • whether they showed signs before birth
  • what symptoms they have now, and when they started

Make sure you understand how accurate their predictions are.

Picture of a young girl playing with a toy stethoscope

Is a person’s DNA code stored after genetic testing?

The lab often reads a person’s complete DNA code when they have a genetic test for ARPKD. This is called ‘whole genome sequencing’. Although the machine reads all the DNA, the lab will only look at the genes linked to ARPKD and other kidney conditions.  

Your doctor may ask if your (or your child’s) full DNA code can be stored in the National Genomic Research Library. This is done anonymously (meaning your name is not stored in the database). Researchers can ask to use the anonymous data in studies about the diagnosis and treatment of diseases.

You can choose whether or not to agree.

Can I have a genetic test for ARPKD at a private clinic?

If you can’t have genetic testing on the NHS, ask your doctor to explain why. It might be that you’re not at risk of having ARPKD.

Some companies offer private genetic testing (meaning it’s not done by the NHS).  You need to pay for this yourself or via health insurance. Before using a private company, ask about the expertise of the lab and the doctor analysing the results.

Genetic tests are technical and the results can be hard to understand. There are over 750 different changes in the DNA code that can cause ARPKD. So, it’s important the service is familiar with them.

What do the genes related to ARPKD do?

The 3 genes associated with ARPKD are codes for 3 different proteins:

  • PKHD1 is the code for fibrocystin
  • DZIP1L is the code for DZIP1L
  • CYS1 is the code for cystin

These 3 proteins are found in cells that line fine tubes in the kidneys. These tubes are where urine (wee) is made.

The proteins are all found in special structures called cilia on the surface of cells. Cilia act like tiny sensors.

Researchers are still working out what jobs these proteins do. It’s possible they help to control how often new cells are made in kidney tubes.

Changes to the DNA code may alter the proteins, stopping them working properly. Sometimes, a DNA change means a protein isn’t made at all.

Experts think cysts might occur when too many cells grow in the kidney tubes. This can make a bulge, which could become a cyst.

Fibrocystin is also found in the liver. When there’s not enough fibrocystin in liver cells, scar tissue can form in the liver (fibrosis).

More from the PKD Charity

Getting more information and support

Authors and contributors

Original version written by Christine Patch, PhD RN, Reader in Genomic Healthcare, King’s College London, in 2016. Updated by Hannah Bridges, PhD, independent medical writer, HB Health Comms Limited, in 2025. Expert review by Dr Shalabh Srivastava, Consultant Nephrologist, City Hospitals Sunderland and South Tyneside NHS Foundation Trust, UK.

With thanks to all those affected by ARPKD who contributed to this publication.

Ref No: ARPKD.GCT.V2.0

Review Date: September 2029

Disclaimer:  This information is primarily for people in the UK. We have made every effort to ensure that the information we provide is correct and up to date. However, it is not a substitute for professional medical advice or a medical examination. We do not promote or recommend any treatment. We do not accept liability for any errors or omissions. Medical information, the law and government regulations change rapidly, so always consult your GP, pharmacist or other medical professional if you have any concerns or before starting any new treatment.

Disclaimer regarding imagery: All photography appearing on this web page is for illustrative purposes only and is freely available via Pexels. The medical history of persons shown is unknown

We welcome feedback on all our health information. If you would like to give feedback about this information, please email [email protected]

If you don't have access to a printer and would like a printed version of this information sheet, or any other PKD Charity information, call the PKD Charity Helpline on 0300 111 1234 (weekdays, 9am-5pm) or email [email protected]

The PKD Charity Helpline offers confidential support and information to anyone affected by PKD, including family, friends, carers, newly diagnosed or those who have lived with the condition for many years.

Read more …Genetic counselling and testing for ARPKD

  • Hits: 21243

Feedback

We welcome feedback on the information provided on this webpage. If you have any feedback regarding the information provided on this webpage, please complete the Feedback Form